
Living with OCD: How Advanced Therapies Are Changing Treatment

Obsessive-compulsive disorder is one of the most misunderstood conditions in psychiatry. Popular culture has reduced it to a quirk, a punchline, or a personality type. The reality for people living with clinical OCD is something far more serious: a relentless cycle of intrusive thoughts and compulsive behaviors that can consume hours of every day, derail careers, strain relationships, and make ordinary life feel impossible. It is also, historically, one of the harder psychiatric conditions to treat effectively. Standard first-line treatments, SSRIs at high doses combined with a specific form of cognitive behavioral therapy called Exposure and Response Prevention, help many patients but leave a significant proportion without adequate relief. That picture is changing. A new generation of advanced treatments, including TMS therapy with an FDA-approved OCD protocol and ketamine therapy, is offering meaningful options to patients who have not responded to standard care. This post covers what those options are, how they work, and how to know whether they might be right for you. Understanding OCD: Beyond the Stereotype OCD is a neurobiological condition characterized by two core features: obsessions and compulsions. Obsessions are unwanted, intrusive thoughts, images, or urges that cause significant distress. They are not simply worries about real-life problems. They are persistent, involuntary mental intrusions that the person experiencing them recognizes as irrational but cannot dismiss. Common obsession themes include contamination and illness, harm to self or others, symmetry and order, religious or moral scrupulosity, and sexual or violent intrusive thoughts. Compulsions are repetitive behaviors or mental acts performed in response to obsessions, with the goal of reducing anxiety or preventing a feared outcome. They provide temporary relief but reinforce the obsessive cycle over time, making the OCD more entrenched rather than less. Common compulsions include hand washing, checking, counting, arranging, seeking reassurance, and mental rituals like praying or reviewing. The defining feature of clinical OCD is not the content of the obsessions or compulsions but the degree to which they consume time and cause distress or functional impairment. By definition, OCD significantly interferes with daily life. Many patients spend four or more hours per day caught in the obsessive-compulsive cycle. Why Standard OCD Treatment Falls Short for Many Patients The gold standard treatment for OCD combines high-dose SSRIs with Exposure and Response Prevention therapy, a structured behavioral treatment in which patients are gradually exposed to their feared triggers while being supported in resisting the compulsive response. ERP is effective. For patients who can access a trained ERP therapist and complete the treatment, response rates are meaningful. But the treatment has real limitations. Trained ERP therapists are not uniformly available. The treatment is demanding and requires significant patient motivation and tolerance for distress. And even with optimal ERP and SSRI treatment, approximately 40 to 60 percent of OCD patients do not achieve adequate symptom relief. For this population, the question of what comes next has historically had very few good answers. That is the gap that advanced treatments are beginning to fill. TMS Therapy for OCD: FDA-Approved and Clinically Meaningful In 2018, the FDA cleared deep TMS therapy for OCD using the Brainsway H7 coil, a milestone that established TMS as a legitimate and evidence-backed treatment option for patients whose OCD has not responded adequately to medication and therapy. The TMS protocol for OCD differs from the depression protocol in an important way. Rather than targeting the left prefrontal cortex as in depression treatment, the OCD protocol targets the anterior cingulate cortex and medial prefrontal cortex, regions of the brain that play a central role in the error-signaling and behavioral inhibition circuits implicated in OCD. The OCD protocol also incorporates a symptom provocation component immediately before stimulation, during which the patient is briefly exposed to their OCD triggers to activate the relevant neural circuits before TMS stimulation is applied. The pivotal trial supporting FDA clearance found that patients receiving active deep TMS for OCD experienced significantly greater symptom reduction than those receiving sham treatment, with 38.1 percent of active treatment patients achieving a clinically meaningful response compared to 11.1 percent in the sham group. Real-world outcomes in clinical settings have generally been consistent with or more favorable than these trial results. TMS for OCD is non-invasive, requires no anesthesia, causes no systemic side effects, and fits into a normal daily routine. Sessions run approximately 20 minutes. Patients drive themselves to and from treatment and return to their normal activities immediately afterward. Ketamine Therapy for OCD Ketamine’s role in OCD treatment is less established than its role in depression, but the emerging evidence is genuinely promising. Several clinical trials have found that IV ketamine produces rapid and meaningful reductions in OCD symptoms, sometimes within hours of a single infusion. The mechanism appears related to ketamine’s effects on glutamate signaling in the cortico-striato-thalamo-cortical circuits that drive OCD symptomatology, circuits that are not directly targeted by serotonergic medications. A 2023 crossover trial found that a single ketamine infusion produced significantly greater OCD symptom reduction than placebo, with effects lasting several days to weeks after the infusion. For patients in acute OCD distress who need rapid relief, or for those who have not responded to TMS or SSRI trials, ketamine represents a meaningful option worth discussing with a psychiatrist. Ketamine for OCD is not yet FDA-approved for that specific indication, meaning it is used off-label. This is the same status ketamine held for depression for many years before its evidence base became too strong to ignore. The trajectory of the research suggests OCD may follow a similar path. Who Is a Good Candidate for Advanced OCD Treatment? Advanced treatments like TMS and ketamine are most appropriate for patients who fit the following profile: You do not need to have tried every possible medication or exhausted every possible therapy before these options are available to you. But a documented history of standard treatment attempts is typically part of the clinical picture that makes advanced treatment appropriate. OCD Treatment at NeuPath Mind Wellness At NeuPath Mind Wellness, we offer both TMS therapy
Why Antidepressants Stop Working and What to Do Next

You found a medication that helped. Maybe it took a few tries to get there, but eventually something worked. Your mood lifted, the weight of depression eased, and for a while you felt like yourself again. Then, gradually or suddenly, it stopped working. This experience has a name. Clinicians call it antidepressant tachyphylaxis, though patients more often describe it simply as their medication pooping out. It is more common than most people realize, affects a significant proportion of patients on long-term antidepressant therapy, and is one of the most frustrating experiences in psychiatric treatment because it raises a question that feels impossible to answer: if the thing that was working has stopped working, what do you do next? This post answers that question directly. Why Antidepressants Stop Working Before exploring what to do next, it helps to understand why this happens. There is no single explanation that applies to every patient, but the most well-supported mechanisms include the following. Neurobiological adaptation. The brain is constantly adjusting to its chemical environment. When an antidepressant increases serotonin availability in the synaptic cleft, the brain responds over time by downregulating serotonin receptors, reducing their number or sensitivity to compensate for the increased stimulation. Eventually this adaptation can offset the therapeutic effect of the medication, even at the same dose. Changes in your biology over time. Depression is not a static condition and neither is the biology underlying it. Hormonal shifts, aging, changes in inflammation levels, metabolic changes, and the natural progression of the illness itself can all alter how your brain responds to a medication that previously worked well. Genetic factors you did not know about. Your liver enzymes, particularly the cytochrome P450 family, play a major role in how quickly your body clears medications from your system. These enzyme activity levels can shift with age, with other medications you start taking, or with changes in diet. A medication that was previously metabolized at an ideal rate may begin clearing too quickly or too slowly over time, taking it out of its therapeutic window. Stress and life circumstances. Major stressors, trauma, grief, relationship changes, and other life events can overwhelm the capacity of a medication that was previously sufficient. The antidepressant has not changed but the load it is being asked to carry has increased beyond what it can manage. The medication was never fully working. Sometimes what felt like a response was a partial improvement or a placebo component that has faded. This is not a moral failing. It is a reflection of how difficult it is to distinguish between a genuine pharmacological response and the natural variability of depression over time. What Not to Do Before covering what works, it is worth addressing the most common unhelpful responses to antidepressant failure, because they are tempting and understandable but rarely productive. Do not simply increase the dose without guidance. Dose escalation is sometimes clinically appropriate but it is not always the answer and can increase side effects without improving efficacy if the underlying issue is adaptation or a genetic mismatch rather than underdosing. Do not stop abruptly. Discontinuing antidepressants suddenly can cause discontinuation syndrome, a cluster of symptoms including dizziness, nausea, flu-like feelings, and mood instability that is often mistaken for relapse. Always taper under psychiatric supervision. Do not assume you are out of options. This is the most important point in this section and arguably in this entire post. A medication stopping working is not evidence that your depression is untreatable. It is evidence that your current approach needs to change. What to Do Next: Your Options Option 1: Optimize Your Current Medication Before switching medications entirely, there are several adjustments worth exploring with your psychiatrist. A dose adjustment, either up or down, may restore efficacy. Timing changes, such as shifting from morning to evening dosing, can affect how the drug is metabolized. Adding a short-term augmentation agent, a second medication that works alongside the antidepressant, is a well-established strategy for restoring response. Common augmentation options include lithium, atypical antipsychotics like aripiprazole or quetiapine, or buspirone. None of these adjustments should be made without psychiatric oversight, but they are often the first reasonable step before moving to a full medication switch. Option 2: Switch to a Different Antidepressant If optimization does not restore response, switching medications is the next logical step. This is where the trial-and-error problem becomes most acute. Without additional information, the choice of which medication to try next is largely educated guesswork. This is exactly the situation GeneSight genetic testing is designed to improve. Option 3: GeneSight Genetic Testing GeneSight analyzes your DNA to identify how your body metabolizes psychiatric medications and how your brain is likely to respond to them. The test produces a color-coded report that categorizes every major antidepressant as likely to work well, likely to require caution, or likely to carry elevated risk based on your specific genetic profile. For patients cycling through failed medication trials, GeneSight can reveal whether genetic factors are contributing to the pattern. A patient who is an ultra-rapid metabolizer of CYP2D6-dependent medications, for example, may have been clearing SSRIs so quickly that they never reached therapeutic concentration, explaining a long history of apparent non-response to multiple drugs in the same class. GeneSight does not guarantee that the next medication will work. But it replaces guesswork with data, and for patients who have already spent months or years on medications that were never a good genetic match, that shift in approach can be genuinely transformative. GeneSight testing is available at NeuPath Mind Wellness across all three of our South Florida locations and is covered by many insurance plans including Medicare. Option 4: TMS Therapy If medication optimization and switching have not produced adequate relief, Transcranial Magnetic Stimulation is one of the most well-supported next steps available. TMS is FDA-approved for treatment-resistant depression and works through an entirely different mechanism than antidepressants. Rather than altering brain chemistry through the bloodstream, TMS uses focused magnetic pulses to directly stimulate the neural
One-Day TMS: Can You Really Treat Depression in a Single Day?
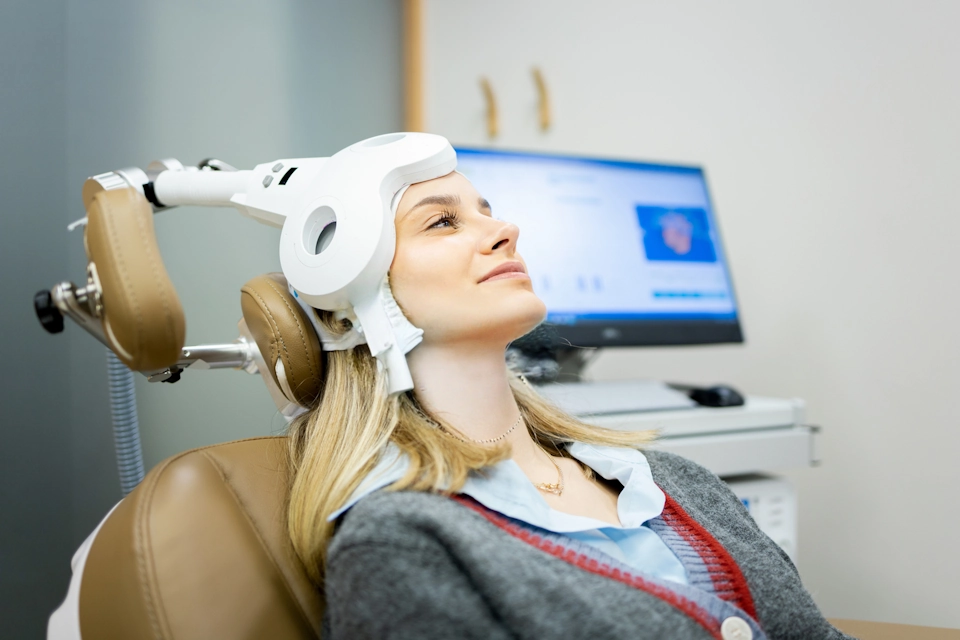
When most people hear that TMS therapy takes four to six weeks of daily sessions, their first reaction is one of two things: relief that there is finally an effective option, or immediate concern about whether they can realistically fit that into their life. Work schedules, family responsibilities, travel, and the simple logistical reality of five clinic visits per week for over a month can make a standard TMS course genuinely difficult for many patients. For some, it becomes the reason they delay treatment or do not pursue it at all. One-Day TMS exists to solve that problem. At NeuPath Mind Wellness, we offer an accelerated TMS protocol that compresses a full course of Transcranial Magnetic Stimulation into a single intensive day of treatment. The same FDA-cleared technology. The same therapeutic target. A fraction of the time commitment. This post explains what One-Day TMS is, how it works, what the research behind it says, and how to know whether you are a good candidate. What Is One-Day TMS? One-Day TMS is an accelerated TMS protocol that delivers multiple TMS sessions across a single day with short rest intervals between them. Rather than spreading stimulation across 36 daily sessions over six weeks, the treatment concentrates the therapeutic dose into a condensed format completed in one clinic visit. The concept is grounded in a growing body of research into accelerated TMS, which has established that the brain does not require 24-hour gaps between stimulation sessions to consolidate the neuroplastic changes TMS produces. What matters is the total cumulative dose of stimulation and the quality of each pulse sequence, not the number of calendar days over which it is delivered. This research culminated most prominently in the Stanford SAINT protocol, a form of accelerated theta burst TMS developed at Stanford University that delivered multiple TMS sessions per day over five consecutive days. Clinical trials using the SAINT protocol reported response rates as high as 78 to 90 percent in patients with severe treatment-resistant depression, significantly higher than the 50 to 58 percent typically reported for standard TMS protocols. One-Day TMS takes the same accelerated principle and compresses it further for patients who need results in the shortest possible timeframe. How Is It Different From Standard TMS? Standard TMS delivers one session per day, five days a week, for four to six weeks. Each session uses a pulse pattern called repetitive TMS or rTMS, which stimulates the left prefrontal cortex at a fixed frequency over 19 to 37 minutes. One-Day TMS uses a faster pulse pattern called theta burst stimulation, or TBS. Theta burst delivers the same therapeutic stimulation in a fraction of the time per session, typically three minutes per session rather than 20 to 37. Multiple theta burst sessions are then delivered across the day with short rest intervals in between, allowing the brain to consolidate each round of stimulation before the next begins. The key differences in practice: Time commitment. Standard TMS requires six to seven weeks of weekday clinic visits. One-Day TMS requires one day. Pulse pattern. Standard TMS uses rTMS at 10Hz. One-Day TMS uses intermittent theta burst stimulation, which more closely mimics the brain’s natural rhythms and has shown equivalent or superior outcomes in multiple clinical trials. Session length. Individual theta burst sessions within a One-Day protocol last approximately three minutes each. Multiple sessions are delivered across the day. Flexibility. Standard TMS fits best for patients with stable routines who can commit to a fixed daily schedule. One-Day TMS fits best for patients with demanding or unpredictable schedules, frequent travelers, caregivers, and those who want results without a multi-week commitment. What Does the Research Say? The evidence behind accelerated TMS protocols is substantial and growing rapidly. The Stanford SAINT trial, published in the American Journal of Psychiatry in 2022, treated patients with severe treatment-resistant depression using an accelerated theta burst protocol delivering 10 sessions per day over five days. The results were striking: 78.6 percent of patients met criteria for response and 57.1 percent achieved remission. These numbers significantly outperform the historical benchmarks for standard TMS. A 2023 systematic review and meta-analysis published in Translational Psychiatry analyzed 15 randomized controlled trials of accelerated TMS protocols and concluded that accelerated TMS produced antidepressant effects comparable to or exceeding those of standard TMS, with a faster onset of improvement. A landmark 2024 non-inferiority trial published in JAMA Psychiatry directly compared standard TMS to accelerated theta burst TMS in a large patient sample and found no significant difference in outcomes between the two approaches, confirming that the compressed format does not sacrifice effectiveness for speed. The scientific consensus is clear: accelerated TMS works, and in some patient populations it may work better than the standard format. Who Is a Good Candidate for One-Day TMS? One-Day TMS is not appropriate for every patient, and your NeuPath psychiatrist will help you determine whether it is the right fit for your specific situation. That said, it tends to be an excellent option for patients who fit one or more of the following profiles: Patients with demanding schedules. Professionals, business owners, executives, and anyone whose work makes a five-days-a-week clinic commitment genuinely difficult are strong candidates for the compressed format. Caregivers. Parents of young children, people caring for elderly family members, and others whose daily responsibilities cannot be paused for six weeks often find One-Day TMS the only realistic path to treatment. Frequent travelers. Patients whose work or lifestyle involves regular travel cannot reliably maintain the consecutive daily schedule that standard TMS requires. One-Day TMS removes that barrier entirely. Patients who need faster results. While standard TMS produces improvement over four to six weeks, One-Day TMS can initiate a therapeutic response significantly faster. For patients in meaningful distress who want relief as soon as possible without the intensity of IV ketamine, this is a compelling option. Patients who have previously completed standard TMS. Some patients who responded well to a standard TMS course in the past use One-Day TMS as a maintenance or booster
How Many TMS Sessions Do You Need for Depression?
If you are considering TMS therapy for depression, one of the first practical questions you will ask is how long it actually takes. How many sessions? How often? How many weeks out of your life are we talking about? These are the right questions to ask before you commit, and the answers are more straightforward than you might expect. This post covers everything you need to know about TMS session numbers, frequency, duration, and what happens after your initial course ends. The Standard TMS Course A standard TMS course for depression consists of 36 sessions delivered five days a week, Monday through Friday, over approximately six to seven weeks. Some protocols are slightly shorter, running 20 to 30 sessions over four to five weeks, depending on the specific TMS system being used and your psychiatrist’s clinical judgment. The five-days-a-week frequency is not arbitrary. TMS works through neuroplasticity, the process by which the brain builds and strengthens neural connections through repeated stimulation. Consistent, frequent sessions are what drive that process forward. Spacing sessions too far apart reduces the cumulative effect and diminishes outcomes. Each individual session runs between 19 and 37 minutes depending on the protocol. You arrive, sit in the treatment chair, complete the session, and leave. No recovery time, no downtime, no disruption to the rest of your day. Why the Number of Sessions Varies Not every TMS course looks identical. Several factors influence how many sessions your psychiatrist recommends: The TMS system and protocol. Different FDA-cleared TMS devices use different pulse patterns and frequencies. The NeuroStar system, for example, uses a standard protocol of 36 sessions. Brainsway Deep TMS uses a similar course length. Newer theta burst stimulation protocols can deliver equivalent therapeutic effects in sessions as short as three minutes, which is why accelerated formats have become increasingly viable. Your diagnosis and symptom severity. Patients with more severe or longstanding depression may benefit from a full 36-session course rather than a shorter one. Patients whose symptoms begin responding early may reach remission before the course is complete, though most psychiatrists recommend completing the full course regardless to consolidate the gains. Your response to previous treatments. Patients who have tried multiple antidepressants without success, the classic treatment-resistant profile, sometimes benefit from a longer initial course or a higher stimulation intensity compared to patients who are trying TMS as a first alternative to medication. Whether you are combining TMS with other treatments. At NeuPath, some patients receive TMS alongside ketamine therapy or Spravato as part of an integrated treatment plan. The combination can influence the optimal TMS course length. When Will You Start Feeling Better? This is the question behind the question for most patients. The session count matters partly because it tells you how long you will be waiting to feel relief. The honest answer is that TMS improvement is gradual and builds over the course of treatment rather than arriving suddenly. Here is a general timeline based on what most patients experience: Weeks one and two. Most patients notice little to no change during this period. The brain is beginning to respond to stimulation but the changes are not yet clinically meaningful. This is normal and expected. It does not mean the treatment is not working. Weeks three and four. This is where most patients begin to notice something. Sleep often improves first. The flat, heavy quality of depression may begin to lift slightly. Motivation or energy may return in small increments. Some patients notice that their mood is a little more variable, which after a long period of flat depression can itself feel significant. Weeks five and six. For patients who will respond to TMS, meaningful improvement is typically evident by this point. Depressive symptoms are measurably reduced. Some patients reach full remission within the standard course. After the course ends. TMS results continue to develop even after treatment concludes. The neuroplastic changes initiated during the course consolidate over the following weeks and months. Many patients report that their best outcomes came four to six weeks after their final session. What If You Do Not Respond Within the Standard Course? Not every patient responds to a standard TMS course, and it is important to know what options exist if that happens to you. Extended courses. Some psychiatrists recommend additional sessions beyond the standard 36 if a patient is showing partial improvement but has not yet reached an adequate response. Insurance coverage for extended courses varies by plan and requires clinical justification. Protocol adjustments. If your initial course used a standard TMS protocol without sufficient response, switching to a deep TMS protocol or a theta burst stimulation format may produce different results. The two approaches stimulate the brain differently and some patients respond better to one than the other. Combination approaches. At NeuPath, patients who have a partial TMS response sometimes move to ketamine therapy or Spravato to build on the gains TMS has initiated. The two treatments work through different mechanisms and can complement each other in ways that neither achieves alone. Re-evaluation. Sometimes a lack of response points to a need for a fuller diagnostic picture. GeneSight genetic testing, available at NeuPath, can identify whether there are pharmacogenomic factors affecting your response to both medications and treatments, and help your psychiatrist refine the overall approach. What About Maintenance Sessions? TMS produces durable results for most patients, but depression is a chronic condition for many people and symptoms can return over time. Maintenance TMS is a recognized and commonly used strategy for sustaining the benefits of an initial course. Maintenance looks different for different patients. Some people return for a booster course of 5 to 10 sessions once or twice a year when they notice early warning signs of a relapse. Others do a monthly maintenance session as a preventive measure. There is no single standard protocol for maintenance, and the right approach depends on your individual history and how your depression tends to behave over time. The practical advantage of maintenance TMS over maintenance
What to Expect During Your First TMS Therapy Session

Starting any new medical treatment comes with questions. What will it feel like? How long does it take? Will it hurt? What happens if I react badly? These are completely reasonable things to wonder about, and for most people considering TMS therapy, the uncertainty around the experience itself is one of the biggest barriers to taking the first step. The good news is that TMS is one of the most straightforward treatment experiences in modern psychiatry. No anesthesia, no recovery time, no altered states, and no need to clear your schedule around it. Most patients tell us that after their first session, the main thing they feel is relief that it was so much simpler than they expected. This post walks you through exactly what happens, from the moment you arrive to the moment you leave, so there are no surprises. Before Your First Session: The Initial Evaluation TMS does not begin on the first day you walk in. Before any treatment starts, you will have a full psychiatric evaluation with one of our NeuPath clinicians. This is not a formality. It is a genuinely important step that shapes everything that follows. During this evaluation your psychiatrist will review your full psychiatric history, including previous diagnoses, medications you have tried, and how your symptoms have evolved over time. They will also screen for any contraindications to TMS, the most important of which is metal implants in or near the skull, such as cochlear implants, deep brain stimulators, or aneurysm clips. Dental fillings, braces, and joint replacements elsewhere in the body are not a concern. You do not need to fast beforehand. You do not need to stop any medications unless your psychiatrist specifically advises it. You do not need to arrange for anyone to drive you. You can come in, have the evaluation, and drive yourself home afterward exactly as you would after any other medical appointment. If you are also being considered for insurance coverage, this evaluation is where the clinical documentation that supports your prior authorization begins. Mapping Your Brain: The Motor Threshold Test On your first actual treatment session, before the coil delivers a single therapeutic pulse, your technician will perform what is called a motor threshold test. This sounds technical but is completely painless and takes only a few minutes. The motor threshold test determines the precise level of magnetic stimulation your brain responds to. Everyone’s brain is slightly different, and the dose of TMS needs to be calibrated to your individual neurology rather than applied at a fixed setting. To find your threshold, the technician positions the coil over the area of your scalp that corresponds to the motor cortex, the region that controls hand movement, and gradually increases the pulse intensity until your thumb or fingers produce a small, involuntary twitch. That twitch is the signal. It tells your technician exactly how much magnetic stimulation your brain needs to respond, and your therapeutic dose is then calculated as a percentage of that threshold. The result is a precisely personalized treatment, not a one-size-fits-all setting. This calibration is repeated periodically throughout your treatment course if your hair length changes significantly, since even a few centimeters of additional distance between the coil and your scalp can affect the dose. The Treatment Session Itself Once your threshold is mapped, the actual treatment begins. Here is what the experience looks like from start to finish. You sit in a comfortable chair. The TMS chair is reclined like a dentist’s chair but considerably more comfortable. You remain fully clothed. There is nothing to change into and nothing attached to your body. The coil is positioned against your scalp. Your technician places the TMS coil, a device roughly the size and shape of a figure-eight paddle, gently against the left side of your head. It rests on the surface of your scalp and does not apply pressure or cause any discomfort at the point of contact. The pulses begin. You will hear a rapid clicking or tapping sound as the coil activates. Simultaneously you will feel a light tapping sensation on your scalp in the area where the coil is positioned. Most patients describe it as a woodpecker-like sensation, rhythmic and localized. It is not painful for most people, though it can feel unfamiliar or slightly intense in the first couple of sessions before you adjust to it. You stay fully awake and alert. There is no sedation, no medication administered, and no altered state of any kind. You can listen to music, watch something on your phone, or simply sit quietly. Some patients use the time to meditate. Others catch up on podcasts. The session does not require your active participation beyond sitting still. The session ends. A standard TMS session runs between 19 and 37 minutes depending on the protocol being used. NeuPath also offers accelerated TMS formats including our One-Day TMS option for patients who need a compressed timeline. When the session is complete, the coil is removed, you stand up, and you leave. That is the full experience. What You Might Feel During the Session The most common sensations during TMS are: Scalp tapping. The magnetic pulses create a rhythmic tapping feeling on the skin directly under the coil. This is the most universal part of the experience and diminishes noticeably after the first week as your scalp adjusts. Jaw or facial muscle movement. Some patients notice subtle, involuntary twitching in the jaw or facial muscles during certain pulse sequences. This is normal, harmless, and typically reduces as the technician fine-tunes the coil position. A mild headache. Some patients, particularly in the first few sessions, develop a light tension headache that resolves within an hour or so after the session. Over-the-counter pain relief works fine if needed. This side effect tends to fade after the first week. What you will not feel: dizziness, nausea, sedation, cognitive impairment, or anything that would prevent you from driving, working, or carrying on with your day. TMS has no
Is TMS Therapy Covered by Insurance in Florida?

One of the first questions patients ask when they learn about TMS therapy is whether their insurance will cover it. It is a reasonable question, and the answer is better than most people expect. Yes, TMS therapy is covered by insurance for many patients in Florida. Most major insurance plans, including Medicare, cover TMS for treatment-resistant depression, and NeuPath Mind Wellness handles the verification and prior authorization process on your behalf so you are not navigating it alone. Here is everything you need to know about how TMS insurance coverage works, which plans cover it, and what to do if you are not sure whether your plan qualifies. Why Insurance Covers TMS TMS has a distinct advantage over ketamine infusion therapy when it comes to insurance: it is not an off-label treatment. TMS received its first FDA approval for depression in 2008, and the evidence base has grown considerably since then, with additional approvals for OCD, anxious depression, and smoking cessation following in subsequent years. Because TMS is FDA-approved specifically for depression and has a well-established clinical track record, insurance companies have established formal coverage policies for it. This is fundamentally different from IV ketamine, which is used off-label for depression and therefore not covered by insurance. Spravato, the FDA-approved nasal spray form of esketamine, is similarly covered by insurance for the same reason that TMS is: formal FDA approval for the specific condition being treated. If cost has been a barrier to exploring TMS, the insurance coverage picture is worth revisiting. Which Insurance Plans Cover TMS in Florida? Coverage policies vary by plan, but TMS is covered by most major commercial insurers as well as Medicare. Plans that commonly cover TMS include: If your plan is not on this list, it does not necessarily mean you are without coverage. Many additional plans cover TMS either as an in-network or out-of-network benefit. Contact our office at 561-847-3662 and our team will verify your specific plan directly. TMS at NeuPath Mind WellnessNeuPath Mind Wellness offers TMS therapy at all three of our South Florida locations in Delray Beach, Boca Raton, and Boynton Beach. We accept most major insurance plans and work directly with insurers to handle prior authorization before your treatment begins. If you have been living with depression and antidepressants have not given you the relief you were hoping for, TMS may be covered by your insurance and available sooner than you think. Our team is here to help you figure that out. Call us at 561-847-3662 or book a free consultation online to verify your coverage today.
TMS vs. Ketamine for Treatment-Resistant Depression: How to Choose

If you have been diagnosed with treatment-resistant depression, your psychiatrist has likely mentioned two names: TMS and ketamine. Both are available at NeuPath Mind Wellness, both have strong clinical track records, and both are designed specifically for people who have not gotten adequate relief from standard antidepressants. So how do you choose between them? The honest answer is that there is no single right answer that applies to every patient. TMS and ketamine work differently, feel different, fit different lifestyles, and tend to suit different clinical profiles. What the right choice looks like depends heavily on your specific situation, your history, and what matters most to you. This post will walk you through exactly how these two treatments compare so that when you sit down with a psychiatrist, you already have a solid foundation for that conversation. How They Work: Two Completely Different Mechanisms The first thing to understand is that TMS and ketamine are not variations of the same treatment. They are fundamentally different approaches to the same problem. TMS, or Transcranial Magnetic Stimulation, uses focused magnetic pulses delivered through a coil placed gently against your scalp to stimulate the area of the brain responsible for mood regulation. You are fully awake throughout the session. There is no drug involved, no altered state, and no recovery time. TMS works through neuroplasticity, the brain’s ability to build and strengthen neural connections over time. Each session builds on the previous one, and the results develop gradually and durably over the course of treatment. Ketamine works through an entirely different route. It is administered either as an IV infusion or, in the case of Spravato, as a nasal spray under clinical supervision. It works by blocking NMDA receptors in the brain and triggering a rapid surge in glutamate signaling, which jump-starts the growth of new synaptic connections. The antidepressant effect can appear within hours of the first session, which is one of ketamine’s most significant advantages. The Speed Difference This is often the most important factor for patients in the early stages of deciding. Ketamine is one of the fastest-acting antidepressant treatments in existence. Many patients feel a meaningful shift in mood within 24 to 48 hours of their first infusion. For someone in the middle of a severe depressive episode, that speed can be genuinely life-changing. TMS does not work that fast. The typical course runs four to six weeks, and most patients begin noticing improvement somewhere in the second or third week. The results build progressively rather than appearing quickly. If you are in acute distress and need relief as soon as possible, ketamine has a clear advantage on this dimension. If your situation is serious but not a crisis, and you are willing to invest in a treatment course that builds steadily, TMS is a strong option. What the Session Experience Is Like The day-to-day experience of these two treatments is very different, and for many patients this matters as much as the clinical data. A TMS session lasts between 19 and 37 minutes. You sit in a comfortable chair while a coil delivers a series of magnetic pulses to your scalp. You hear a clicking sound and feel a light tapping sensation. That is essentially the full experience. When the session ends, you drive yourself home, go to work, pick up your kids, or do whatever you had planned. There is no altered state, no impairment, and no recovery period needed. A ketamine infusion is a different kind of session. IV ketamine is administered over about 40 to 60 minutes in a monitored clinical environment. Most patients experience a dissociative state during the infusion, a dreamlike, floaty feeling that some find deeply therapeutic and others find disorienting. After the infusion, you need a recovery period before you can leave and you cannot drive yourself home. Plan to have someone with you. Neither experience is inherently better. Some patients find the ketamine infusion to be a meaningful, even profound experience that contributes to the therapeutic effect. Others strongly prefer the straightforwardness of TMS. Your lifestyle and preferences are legitimate factors in this decision. Side Effects: What to Expect From Each TMS has a minimal side effect profile. The most common complaints in early sessions are mild scalp tenderness and a light headache, both of which typically resolve within an hour and diminish after the first week as your scalp adjusts. There are no systemic side effects because TMS does not enter your bloodstream. Your sleep, appetite, sexual function, and cognitive performance are unaffected. Ketamine can cause nausea, dizziness, and elevated blood pressure during or shortly after infusions. The dissociative experience, while tolerated well by most patients, is not comfortable for everyone. These effects are temporary and resolve after the session. Ketamine does not carry the long-term systemic side effects associated with antidepressants, but the in-session experience is more physically and perceptually intense than TMS. How They Compare on Effectiveness Both treatments work. The evidence base for each is substantial. TMS achieves response rates of approximately 50 to 58 percent in patients with treatment-resistant depression, with remission in roughly 30 percent. Newer accelerated protocols have shown significantly higher numbers in clinical trials. Results tend to be durable, with many patients maintaining improvement for a year or more after completing a course. Ketamine produces response rates in the range of 50 to 70 percent depending on the patient population and protocol. Its advantages are the speed of onset and the ability to rapidly interrupt a severe depressive episode. The main challenge with ketamine is that the effects can diminish over time without maintenance infusions, meaning some patients need periodic booster sessions to sustain their improvement. One consideration worth noting: for patients who have tried ketamine and had a partial response, TMS can sometimes build on that improvement. And for patients who complete TMS and want to maintain their results or address a relapse, ketamine can serve as an effective bridge. The two treatments are not mutually exclusive at NeuPath, and
TMS vs. ECT: What’s the Difference? (And Why They’re Not the Same Thing)

If you’ve been researching treatment options for depression and came across TMS (Transcranial Magnetic Stimulation), there’s a good chance someone in your life said something like: “Isn’t that basically shock therapy?” It’s one of the most common misconceptions we hear at NeuPath Mind Wellness. And we understand where it comes from. Both TMS and ECT (Electroconvulsive Therapy) involve the brain. Both are used when antidepressants haven’t worked. That’s largely where the similarities end. The confusion between the two treatments has kept some people from exploring TMS, a safe, non-invasive, and highly effective option for treatment-resistant depression. This post is here to set the record straight. What Is ECT (Electroconvulsive Therapy)? ECT has been around since the 1930s and carries significant cultural baggage, much of it shaped by outdated portrayals in films like One Flew Over the Cuckoo’s Nest. The reality of modern ECT is far less dramatic than Hollywood suggests, but it is still a procedure that requires general anesthesia and involves deliberately inducing a brief seizure in the brain using electrical current passed through electrodes placed on the scalp. ECT is typically reserved for the most severe, life-threatening cases of depression: patients who are acutely suicidal, catatonic, or who have not responded to multiple other treatments. It can be highly effective in those circumstances, but the profile of side effects is significant. Memory loss, particularly short-term, is common and can be lasting. Because of the anesthesia requirement, it must be performed in a hospital or clinical setting with full medical supervision. ECT is not a casual treatment. It is a serious medical intervention used when very few other options remain. What Is TMS (Transcranial Magnetic Stimulation)? TMS is a fundamentally different technology and a fundamentally different experience. Instead of electrical current passed directly through the skull, TMS uses focused magnetic pulses, similar in strength to those used in an MRI machine, to gently stimulate specific regions of the brain associated with mood regulation, particularly the prefrontal cortex. The magnetic field passes through the scalp and skull painlessly to reach the targeted neural tissue. There is no anesthesia. No seizure. No hospitalization. Patients sit in a comfortable chair, remain fully awake and alert throughout the session, and can drive themselves home afterward. Most sessions at NeuPath take between 3 and 19 minutes depending on the protocol being used. Many patients read, listen to music, or simply relax during treatment. TMS received FDA clearance for the treatment of Major Depressive Disorder in 2008 and has since been cleared for OCD, anxious depression, and smoking cessation as well. It has an extensive clinical track record spanning well over a decade. TMS vs. ECT: A Side-by-Side Comparison TMS ECT How it works Magnetic pulses stimulate targeted brain regions Electrical current induces a controlled seizure Anesthesia required? No Yes, general anesthesia Setting Outpatient clinic Hospital or supervised clinical facility Seizure induced? No Yes, intentionally Memory side effects? Rare; not associated with memory loss Memory loss is common, sometimes lasting Patient experience Awake, alert, sitting in a chair Unconscious during procedure Typical session length 3–19 minutes 15–30 minutes (plus recovery time) Who it’s for Treatment-resistant depression; patients who haven’t responded to antidepressants Severe, life-threatening cases; last-resort situations Recovery time None, drive yourself home Hours of recovery; cognitive fog common FDA cleared? Yes, depression, OCD, anxious depression Yes, severe depression 5 Misconceptions About TMS We Hear All the Time 1. “TMS is just a newer version of shock therapy.” No. They use entirely different mechanisms. ECT passes electrical current to trigger a seizure. TMS uses magnetic fields to stimulate neurons. No current enters the brain, no seizure occurs. They are distinct technologies that happen to target the same organ. 2. “TMS will affect my memory.” Memory loss is not associated with TMS. This is a side effect specific to ECT. The most commonly reported side effects with TMS are mild scalp discomfort or a slight headache during the first few sessions, which typically resolves on its own. 3. “I’ll be knocked out during TMS.” You won’t. You’ll be wide awake the entire time. Most patients are surprised by how routine it feels. 4. “TMS is experimental.” TMS has been FDA-cleared since 2008, nearly two decades of clinical use. It is covered by most major insurance plans, including Medicare, for qualifying patients with treatment-resistant depression. 5. “If antidepressants didn’t work, nothing will.” This is perhaps the most damaging misconception of all. Treatment-resistant depression, typically defined as failing two or more antidepressant trials, is exactly the patient TMS was designed for. Clinical studies show that roughly half of treatment-resistant patients experience significant improvement with TMS, and about a third achieve full remission. Why TMS Is a Turning Point for Many Patients For patients who have spent years cycling through medications, adjusting doses, managing side effects, and waiting months to know whether a drug is even working, TMS offers something genuinely different. It targets the brain directly, without the systemic effects of medication. There’s no weight gain, no sexual dysfunction, no emotional blunting, no drug interactions to manage. And unlike ECT, it fits into a normal life. Patients come in before work, after school pickup, on a lunch break. They leave alert and functional. Over a typical course of treatment, usually four to six weeks, many begin noticing meaningful shifts in mood, energy, and motivation. At NeuPath Mind Wellness, we also offer One-Day TMS, an accelerated protocol that condenses treatment into a single intensive session for patients who need faster results or face scheduling barriers. It’s one more way TMS continues to evolve as a flexible, patient-centered treatment. Is TMS Right for You? TMS is not for everyone. Patients with certain metal implants near the head or a history of seizure disorders may not be candidates. The right way to find out is a thorough consultation with a qualified provider who can review your history and treatment background. What we can say is this: if you’ve been told your depression is “treatment-resistant,” or if you’ve tried antidepressants and
What Is TMS Therapy and How Does It Work?
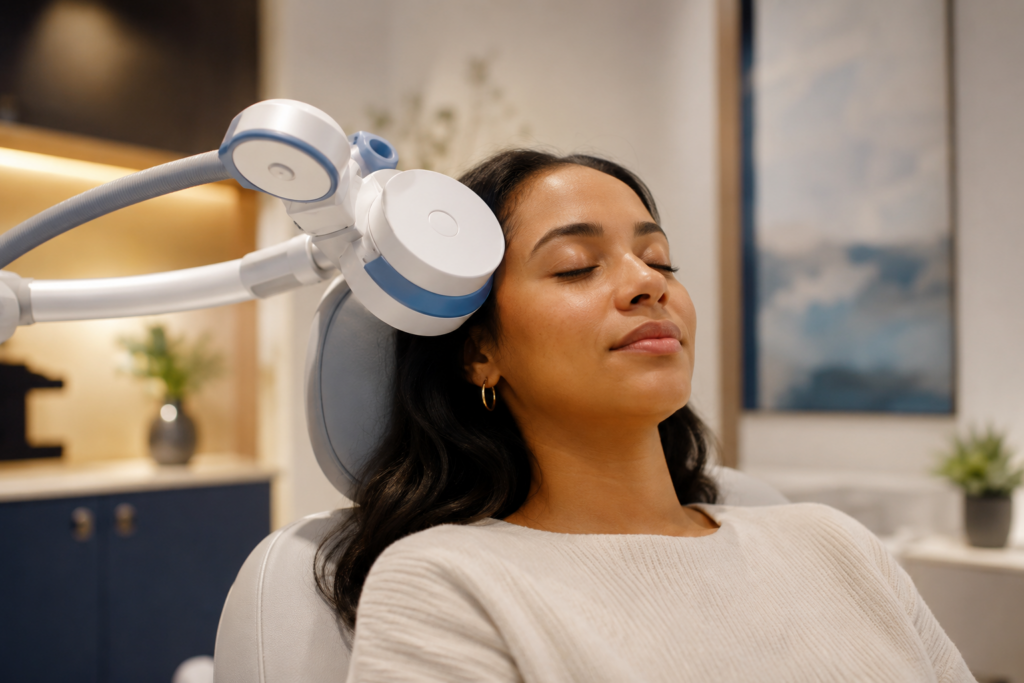
If you have been struggling with depression and antidepressants have not given you the relief you were hoping for, you are far from alone. Nearly one in three people with depression do not respond adequately to standard antidepressant medications. For many of those patients, the search for something that actually works leads them to a treatment they may not have heard of before: TMS therapy. TMS, or Transcranial Magnetic Stimulation, is an FDA-approved, medication-free treatment for depression that uses gentle magnetic pulses to stimulate specific areas of the brain. It is non-invasive, well-tolerated, and backed by decades of clinical research. At NeuPath Mind Wellness in Delray Beach, TMS is one of our most effective tools for helping patients reclaim their mental health. In this post, we will explain what TMS therapy is, how it works, what to expect from treatment, and how to know if it might be right for you. At a Glance TMS Therapy Full form Transcranial Magnetic Stimulation FDA approval Approved for depression (1998), OCD (2018), anxious depression (2021) Treatment type Non-invasive, medication-free brain stimulation Session length 19 to 37 minutes (standard); as short as 3 minutes (accelerated) Typical course 20 to 36 sessions over 4 to 6 weeks Common side effects Mild scalp discomfort, light headache; typically resolves quickly Insurance coverage Often covered for treatment-resistant depression Available at NeuPath Delray Beach, Boca Raton, and Boynton Beach What Is TMS Therapy? Transcranial Magnetic Stimulation is a brain stimulation therapy that uses magnetic fields to activate nerve cells in areas of the brain that regulate mood. The technology is similar in principle to an MRI machine, but the pulses are far more focused and are delivered to a specific target region. The FDA first approved TMS for depression in 2008 and has since expanded its approval to include OCD, anxious depression, and smoking cessation. It is now used in thousands of clinics across the United States as a mainstream treatment for patients who have not responded to medication. Unlike antidepressants, which work by altering brain chemistry through your bloodstream, TMS works directly at the level of the brain. It does not require anesthesia, does not involve any incisions, and has no systemic side effects. Most patients drive themselves to and from their sessions and return to their normal routine immediately afterward. TMS is not a last resort. At NeuPath Mind Wellness, we view it as a first-line option for many patients, particularly those who want an effective, medication-free path to treating depression. How Does TMS Therapy Work? TMS works by targeting the left prefrontal cortex, the area of the brain most associated with mood regulation. In people with depression, this region tends to be underactive. TMS uses a coil placed gently against the scalp to deliver precisely controlled magnetic pulses that pass through the skull and stimulate the nerve cells in that area. Think of it like jump-starting a part of the brain that has gone quiet. Each session delivers thousands of these pulses, and over the course of a full treatment course, the cumulative effect is a lasting improvement in neural activity and connectivity. This process is called neuroplasticity, and it is the same mechanism the brain uses to form habits, learn new skills, and recover from injury. The Role of Neuroplasticity Neuroplasticity is the brain’s ability to reorganize itself by forming new neural connections. TMS harnesses this ability by repeatedly stimulating dormant pathways until the brain learns to activate them on its own. This is why TMS takes a course of treatment to work rather than producing an immediate effect like a sedative might. The changes it creates are structural, not just chemical, which is one reason its results tend to be durable. Research published in major psychiatric journals has confirmed that TMS produces measurable changes in brain connectivity and metabolism, particularly in the prefrontal cortex and its connections to the limbic system, which governs emotional response. TMS vs. Standard Antidepressants: A Different Mechanism Standard antidepressants like SSRIs and SNRIs work by altering the levels of neurotransmitters such as serotonin and norepinephrine across the entire brain and body. This is why they can take 4 to 6 weeks to show results and often come with side effects like weight gain, fatigue, and sexual dysfunction. TMS bypasses the bloodstream entirely. It works locally and directly on the brain tissue without affecting the rest of the body. This means no systemic side effects, no waiting weeks for medication to build up, and no need to taper off when treatment ends. For patients who are sensitive to medications or who have struggled with side effects, this difference is significant. What Conditions Does TMS Treat? TMS was originally developed for depression, but research has expanded its application considerably. At NeuPath Mind Wellness, we use TMS to treat the following conditions: The most common application. TMS is particularly effective for patients who have tried two or more antidepressants without adequate relief. The FDA specifically approved a TMS protocol for depression with comorbid anxiety in 2021. Many patients experience both conditions simultaneously, and TMS can address both. TMS received FDA clearance for OCD in 2018. A deep TMS protocol targeting the anterior cingulate cortex has shown strong results for patients whose OCD has not responded to medication. While TMS is not yet FDA-approved specifically for PTSD, clinical evidence and real-world results strongly support its use. Many patients at NeuPath experience meaningful reduction in PTSD symptoms through TMS, often in combination with other therapies. Generalized anxiety, social anxiety, and panic disorder have all shown responsiveness to TMS protocols targeting the prefrontal cortex and related brain regions. What to Expect During a TMS Session If you have never had TMS before, walking into your first session can feel unfamiliar. Here is a step-by-step picture of what actually happens. Before Your First Session Your NeuPath psychiatrist will conduct a full evaluation to confirm that TMS is appropriate for your situation. This includes a review of your psychiatric history, any medications you are currently taking,